
Third Term Project: Gilgil Sub-County, Nakuru County, Republic of Kenya
From June 2023 to May 2026, SHIONOGI and World Vision Japan implemented a project in Kiambogoko, Gilgil Sub-County, Nakuru County, Republic of Kenya, to improve the health of pregnant and breastfeeding women and children under five.
Working through two health centers and two dispensaries, we improved health facilities, strengthened the capacity of healthcare workers, and conducted education and awareness-raising activities for community members. Through these activities, we worked to improve the quality of maternal and child health services and promote a sustainable, community-led health system that supports the health of mothers and children.


Support project outline
| Location | Kiambogoko, Gilgil Sub-County, Nakuru County, Republic of Kenya |
|---|---|
| Target population | 34,643 (direct beneficiaries: 13,035; indirect beneficiaries: 21,608) |
| Term | June 2023 to May 2026 |
| Budget | 76 million yen |
| Partner | World Vision Japan (a specified non-profit corporation) |
Project location


Healthcare issues for mothers and children in Kiambogoko
Concentration of patients at a particular health facility (Insufficient capacity)
Households with latrine
24%
Households getting water from improved water sources
9%
Lack of resources for community health in the county government


The support area has problems such as a delay in infrastructure development for health facilities and crowded of patients at one health center from all over the area. These problems have resulted in the situation where community people are unable to receive sufficient basic medical services when needed.
Other challenges include child nutritional status, such as stunting and underweight, and low access to improved sanitation facilities. Regarding water hygiene, diarrhea in children is also an issue.
Health data (reference values)
| Indicator | Kenya※1 | Kiambogoko※2 |
|---|---|---|
| Antenatal care coverage (four or more times) | 58% | 52% |
| Birth attended by skilled health personnel/Deliveries at health facilities | 61.2% | 82% |
| Full vaccination coverage | 67.5% | 85% |
| Cases of diarrhea among children under 5 years old | - | 1,176 cases |
| Access to improved water | - | 9% |
- ※1Kenya Demographic Health Survey 2014
- ※2World Vision Survey 2021
Four Initiatives to Address the Challenges
Building on the approaches used in previous M2M projects and reflecting the local context in Kiambogoko, we worked to improve Maternal, Newborn and Child Health (MNCH) by improving access to healthcare in remote areas and strengthening community health systems, including Mother to Mother support groups (M2M groups).* We also set the reduction of diarrhea cases among children under five as a specific indicator and placed particular emphasis on Water, Sanitation and Hygiene (WASH) activities.
*Groups in which mothers in each community teach and learn from one another about maternal and child health and nutrition (peer education).
1. Improving Access to Maternal and Child Health Services
To improve access to and the quality of health services for pregnant women, mothers and children, we improved health facilities, strengthened healthcare workers’ capacity, and promoted preventive health education and the use of health services by forming and strengthening Community Health Volunteer (CHV) networks and Mother to Mother groups.。
Key activities
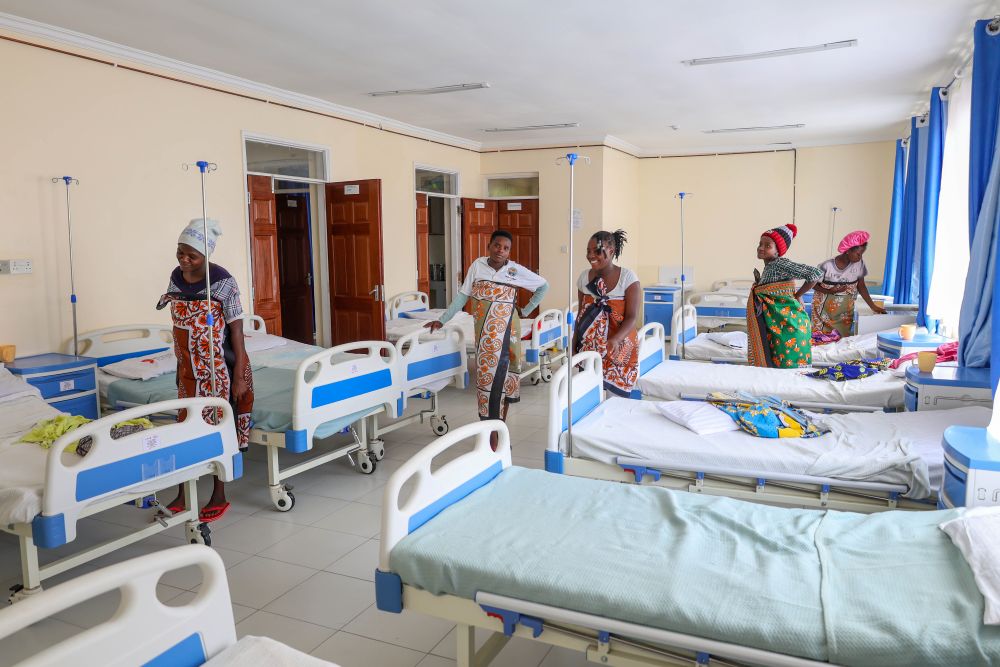
- ・Construction of a maternity block and renovation of an existing block at Kiptangwanyi Health Center
- ・Provision of medical equipment and supplies
- ・Knowledge and skills training for healthcare workers
- ・Supportive supervision
- ・Data management reviews
- ・Integrated outreach services
- ・Household visits and capacity strengthening for CHVs
- ・Formation and strengthening of M2M groups
Construction or renovation of health facilities
2
Healthcare workers trained
32
Participants in M2M groups
809



2. Improving WASH Conditions and Hygiene Practices in Health Facilities and Communities
To reduce diarrhea cases among children under five, we provided WASH training and handwashing education for healthcare workers, CHVs and teachers, focusing on health facilities and schools. We also supported the introduction of water purification methods, implemented Community-Led Total Sanitation (CLTS) activities to address open defecation, and established Oral Rehydration Corners (ORCs)* at health facilities to provide appropriate care for children with diarrhea.
*Oral Rehydration Corner
Key activities
・Establishment of Oral Rehydration Corners at health facilities
・WASH training for teachers
・Establishment and training of school health clubs
・Training and monitoring to address open defecation
・WASH awareness-raising for community members
Health facilities with an ORC
4School health clubs
22 clubs / 12 schoolsHousehold WASH surveys
46 villages



3. Improving Nutrition Practices among Community Members
We provided nutrition training for healthcare workers and CHVs, cooking demonstrations, and nutrition education through M2M groups, while promoting awareness of maternal and child health and nutrition. We also strengthened community- and facility-based screening and referral systems for the early identification and support of children with acute malnutrition.
Key activities
・Support for nutrition activities in M2M groups
・Nutrition screening for children under five
・Follow-up of children with acute malnutrition
・Nutrition training for healthcare workers and CHVs
Follow-up visits for children with
acute malnutrition


4. Strengthening Governance for Maternal and Child Health
We promoted community-led advocacy through Citizen Voice and Action and worked with government stakeholders to influence policies and budgets for maternal and child health, nutrition and WASH. We also conducted project monitoring and evaluation, shared results, and held discussions to support the sustainability of project activities.
Key activities
・Community-led advocacy through Citizen Voice and Action
・Stronger collaboration with government stakeholders in MNCH, nutrition and WASH
・Support for participation in government policy and budgeting processes
・Sharing project results and discussing sustainability
・Regular dialogue between government and communities
・Project monitoring and evaluation
Community advocacy group formed
1 group (26 members)
Changes in the Project Area Resulting from Three Years of Activities
By improving the environment supporting maternal and child health services, educating and raising awareness in communities, and establishing community-led systems, the project contributed to changes in the use of health services, health practices and local implementation structures. The main changes over the three years are presented below with key indicators.
1. Improved Access to Maternal and Child Health Services
Improvements to health facilities, training for healthcare workers, community health education through M2M groups, and broader capacity strengthening made essential health services more accessible to pregnant women, mothers and children. Strengthening nearby facilities also helped distribute service users more evenly, reducing concentration at a single facility and enabling more women to receive appropriate care closer to home. Across Gilgil Sub-County, the under-five mortality rate decreased from 50 to 17 per 1,000 live births. The project contributed to this broader improvement in maternal and child health indicators.
Women receiving at least four ANC visits
52% → 79%Achievement against the target for women receiving family planning commodities
70% → 120%Children fully immunized
85% → 90%Births attended by skilled health personnel
82% → 73%**Affected by initial disruptions following the introduction of the Social Health Authority (SHA) in October 2024, shortages of healthcare workers, and insufficient staff housing.
2. Improved WASH Conditions and Hygiene Practices
Continuous awareness-raising in schools and communities improved hygiene practices and reduced diarrhea cases among children.
Handwashing with soap
88.0% → 92.6%Households treating drinking water
70.1% → 91.0%Villages certified Open Defecation Free*
77 / 77 villagesDiarrhea cases among children under five
773 → 613*Certification by government or other authorities that all households in a community use latrines and that open defecation no longer occurs.
3. Improved Nutrition Practices among Community Members
Nutrition training for CHVs and awareness-raising through M2M groups helped expand knowledge and practice of exclusive breastfeeding and appropriate complementary feeding. As a result, the number of underweight cases among children under five decreased.
Underweight cases among children under five
329 → 1274. Strengthened Governance for Maternal and Child Health
To support sustainability, we worked with Nakuru County, Gilgil Sub-County and local health personnel to foster local ownership. Counterparts are expected to continue and further develop the activities after project completion.
Opportunities to provide recommendations
to the Government of Kenya or participate
in policy development
Pick UP
Behavior Change and Self-Reliance among Mothers through Mother to mother Groups
In the target villages, collaboration between CHVs and health centers enabled many pregnant and breastfeeding women to participate in mother to mother groups. The meetings served not only as a platform for CHVs to share maternal and child health information, but also as a forum where experienced mothers shared their knowledge and experience with newer mothers. Women participating in savings groups gained access to low-interest loans and improved household finances through income from individual or group businesses.
Monthly mother to mother group meetings have continued after project completion. More women are applying what they learned, including exclusive breastfeeding and savings practices, recognizing changes in themselves, their children and their households, and actively sharing their experience with other women.

Pick UP
Group Antenatal Care Supporting Maternal Health and Connection
Kiambogo Dispensary introduced Group Antenatal Care, organizing pregnant women by stage of pregnancy and enabling each group to attend antenatal care together once a month. Members began traveling together from their villages, contributing to more consistent attendance.
The sessions also provide a space for pregnant women to share concerns and experiences, enabling psychosocial support among group members. This successful approach is expected to be expanded to other areas.

Voices from the Community
Voices of people involved in and benefiting from the project.
Bernadette Luori, Facility In-Charge, Kiptangwanyi Health Center
“Today is a very special day for us. I'm very happy to be here today. I'm very grateful as a facility in charge and also as a member of the community. Words cannot express our gratitude. The facility will not only improve medical services for patients, but will also contribute to improving the overall health of the community. From today onwards, we will responsibly maintain the facilities and equipment that you have supported to improve and maintain our service standards. And I promise to do my best to provide necessary services to patients. Your support has greatly encouraged us. May you be blessed in abundance.”

Mary, who gave birth at Kiptangwanyi Health Center
“I gave birth to my oldest child in a hospital in Nairobi. Last time, I had to share a bed with two other women in that hospital. This health center is close to my house and new, so this delivery was very comfortable. I had ANC visits 8 times, and the nurse taught me a lot.”

Haron Kurei
WASH Coordinator, Gilgil Sub-County
“Your support has been a true game changer for Gilgil Sub-County. By providing mothers with many learning opportunities, the M2M Project empowers them and promotes healthier lives at home. Healthcare workers are also becoming more confident in providing health services.
Your support is bringing visible change to the lives of mothers and babies. We sincerely thank you for investing in Gilgil Sub-County.”


Voice from a Mother to Mother Group Supported by the Project
“I learned a lot from the M2M group. Knowledge about WASH and savings in particular was a real game changer for us. Women’s cash income has increased, enabling them to afford daily necessities. The number of children suffering from diarrhea has also decreased dramatically.”
